


There are 2 different treatment protocols; the long protocol and the antagonist protocol. We decide which protocol is best for you based on your ovarian reserve tests.
Most women will follow the long agonist protocol. Women with a very high ovarian reserve who have a higher than average risk of developing Ovarian Hyperstimulation Syndrome (OHSS) will follow the antagonist protocol. This is because the antagonist protocol can reduce their chance of developing OHSS.
We will explain your protocol and our reasons for choosing it before you start the medication. You can read more about OHSS.
Step 1 – Suppressing your natural cycle (long protocol only)
Buserelin Acetate (Suprecur) or Nafarelin (Synarel) will temporarily ‘switch off’ your natural cycle to allow us to control the timing of your treatment cycle. This is perfectly safe to do and there is no evidence to suggest it affects your future fertility. We will give you a programme before you commence your treatment cycle that informs you when to start this medication.
Some patients may experience vaginal bleeding when taking Buserelin/Nafarelin. The bleeding can be light or heavy and is not of concern. Buserelin and Nafarelin can cause similar symptoms to the menopause such as headaches, irritability, and fatigue. If you do experience side effects, they should resolve when you start the FSH injections. If you are worried about the side effects of any of your medications, please email the nurses.
Step 2 – Boosting your egg supply
Medication is used to encourage the ovaries to produce more eggs than usual.
Follicle Stimulating Hormone (FSH) injections stimulate the ovaries to produce eggs. Stimulation injections are administered daily under the skin (subcutaneous). Follicles are tiny fluid filled sacs that grow on the ovary and contain the eggs. In your normal monthly cycle, only one egg is produced. To increase the chances of pregnancy with IVF treatment, we need several eggs. The average number of eggs retrieved is eight but can vary between patients depending on your individual ovarian reserve.
Menopur, Meriofert or Ovaleap
Menopur, Meriofert and Ovaleap are forms of Follicle Stimulating Hormone (FSH) used to stimulate the ovaries to produce eggs. You will be prescribed one of these drugs depending on your individual circumstances and the availability of medicines at the time you present for treatment. Occasionally medicines run out of stock and we need to switch to an alternative brand of FSH. We will discuss this with you if it happens.
Menopur, Meriofert or Ovaleap is a daily injection and must be taken at the same time every day (preferably in the morning). It can be used in both the long protocol and the antagonist protocol. It should be kept in a cool, dry place and away from direct heat or sunlight. We will ensure you know how to do the injections when you are ready to commence them. You will be instructed when to start and stop taking the Menopur, Meriofert or Ovaleap injections.
Rekovelle (antagonist protocol only)
Rekovelle injections are only used as part of the antagonist cycle. It is in the form of an injectable pen and must be kept in the fridge. You must take this injection at the same time every day.
Rekovelle is also a form of Follicle Stimulating Hormone (FSH) and the dose is decided based on your weight and AMH levels. This allows us to find a balance between stimulating the ovaries as best we can whilst preventing over stimulation of the ovaries.
When do I start taking the FSH injections?
The expected date for you to start the injections is given on your treatment programme. This date is not set in stone, and it is normal for your cycle not to go exactly according to your programme. The date will be confirmed once you have had a scan to assess the endometrium and ovaries. Some women may also need a blood test prior to starting the FSH injections.
Antagonist protocol only
Cetrotide injections
Cetrotide (cetrorelix acetate) is only used as part of the antagonist cycle and must be kept in the fridge. It is used to suppress ovulation when the follicles have started to develop.
You will be advised when to start the Cetrotide injections. You must take this injection at the same time every day (preferably in the morning). We will instruct you on when to start and stop this medication.
Step 3 – Monitoring your progress and maturing your eggs
We watch the number of eggs growing in your ovaries by doing a series of internal scans. The first scan is usually a week after you start the FSH injections. Your treatment programme will tell you when to attend for a scan however; we will confirm and book the scan in with you.
The egg is microscopic in size and cannot be seen, but it grows in a small cyst or follicle, which shows on the scan as a black shadow. The follicle gets bigger as the egg grows. We will count the number of follicles developing in the ovaries and measure them. When the follicles reach about 16mm in size, we would expect the egg inside to be ready to respond for the next stage of treatment, the trigger injection.
Sometimes the ovaries respond inadequately to the drugs and produce very few, if any, follicles. A decision will be made as to whether the treatment cycle is to be continued, despite the very poor chance of success or cancelled. If the latter option is chosen, you will be offered a consultation to see a doctor during which other treatment options (if there are any) will be discussed. Occasionally a blood test will be needed to confirm the scan results.
Maturing the eggs
You will be asked to take an injection to mature the eggs, this is sometimes referred to as the trigger. It is carefully timed to your egg collection and is usually given in the evening. You will be told when exactly to take the injection after you have the last scan before egg collection. On this day take your usual FSH injection in the morning and continue taking your Buserelin or Cetrotide injections at your usual times until you have the hCG. Do not take any more injections after the trigger injection. You will be given all of these instructions in writing for you to take away with you. Please read it carefully as it also informs you what to bring with you on the day of the procedure.
There are two types of trigger injection. Long protocol patients will be given Ovitrelle. Antagonist protocol patients will be given either Ovitrelle or Buserelin depending on the number of follicles they have grown. The decision-making process regarding this is explained later in this document, in the OHSS section. We will teach you how to do your prescribed trigger injection.
If you are using your partner’s sperm to create embryos he should ejaculate on the day you have your trigger injection and not again until he produces the sample for egg collection.
Can we have sex?
It is fine to have sex during treatment however; you must use barrier contraception, such as condoms, between starting FSH and embryo transfer.
Step 4 – Collecting the eggs and sperm
Egg retrieval
The eggs are retrieved by using a transvaginal ultrasound scan, just like the ones you have had during the last step. A thin needle is passed along the ultrasound scan machine into the ovaries, via the vagina, to remove the eggs.
The procedure is done under sedation to ensure you are comfortable throughout. You will be offered the option of a premedication, called Lorazepam. This is two tablets, one for the night before and one for the morning of procedure to help with nerves if you feel you will be nervous. This is perfectly safe with treatment.
When a decision is made to proceed to egg retrieval, you will be given an admission form and instructions regarding your medicines. Please read this carefully because it will tell you when and where to come and what to bring with you.
If you are a single person seeking treatment, you might want a friend or relative to accompany you on the day of egg retrieval. If you are attending alone, you must arrange for someone to collect you from the recovery area after the egg retrieval and escort you home. You must have someone to stay with you overnight.
What happens when I am admitted?
On admission to the day ward, one of our fertility nurses will carry out a witnessing check with you (and your partner if applicable) to check that all of your details are correct. The nurse will then perform some vital observations including your temperature and blood pressure. You will need to change into a theatre gown. The nurse sedationist and operator will see you to discuss the procedure and answer any of your questions. A small needle will be used to introduce a plastic tube into a vein in your hand or arm. This is called a cannula and is how the medication will be administered to you during the procedure.
Only one person should attend the egg retrieval with you. Partners or friends/relatives are welcome to stay in the unit but we will ask them to sit in the waiting room or leave the clinic once you go into theatre for the procedure. They can join you again when the egg retrieval is finished and you have recovered from the sedation. This is usually 60-90 minutes from the start of the egg retrieval.
What medication will I be given?
When you arrive to the ward we will give you oral Paracetamol. The nurse sedationist will give you two drugs through the cannula in your arm. The first drug is a pain killer (Fentanyl) and the second is a sedative (Midazolam) to make you feel calm and relaxed. You will not be asleep during the procedure but a common side effect of the sedation is that you may not remember the procedure. Some women may need further pain relief such as Entonox gas. We will discuss this with you if needed.
You can also choose to have a pre-medication (Lorazepam) the night before and the morning of the procedure if you are feeling anxious.
If you have any worries or concerns or would just like to talk to the nurse sedationist, you can contact them via the unit phone number.
How are the eggs collected?
Your legs will be put in special supports and you will then have an internal examination and scan. A very fine needle is inserted through your vagina and into the ovary. This is uncomfortable for just a few moments.
We can then drain the fluid from each follicle. The fluid is passed to the embryologist in the next room who will identify and count the eggs and place them in an incubator compartment that is clearly labelled with your name. The procedure is repeated on the other ovary.
The whole procedure lasts for about 10 minutes depending on how many follicles you have grown. We expect to obtain eggs from approximately 70% of follicles. Occasionally the egg recovery rate may be much lower than this as it is not guaranteed that each follicle contains an egg. On rare occasions, no eggs are found in either ovary.
What happens after the eggs have been collected?
You will be taken back to your bed in the recovery area on a trolley. You will feel drowsy following the procedure so will need to stay in the clinic for 1-2 hours.
The sedation drugs may leave you with a dry mouth, you may feel drowsy and you may have the inability to perform complex tasks. As it takes 24 hours for the sedation drugs to wear off completely you should rest at home for this period of time. You must have someone with you at all times until the following morning.
You should not drink alcohol, use electrical equipment or machinery or drive for 24 hours. You should also not sign any legal documents during this time.
If you live more than 40 minutes away from access to emergency care, we advise you to stay locally.
Once you are awake and feeling well enough to go home, the embryologist will visit you to advise how many eggs were retrieved. They will discuss the results of the semen analysis and confirm if they need to do IVF or ICSI to inseminate the eggs.
What will happen after I go home?
It is normal to have some abdominal discomfort. You can take two Paracetamol tablets every 4 hours but be careful not to take any more than 8 tablets in 24 hours. If the pain is severe and persistent or you are vomiting, please telephone the clinic. Brown vaginal spotting or discharge is not uncommon and will usually settle after approximately 48 hours.
We advise you to have a light meal that evening, as you may feel quite bloated.
Remember to start your Cyclogest pessaries before bed and use one every morning and night from the following day.
The pessaries should be inserted vaginally or rectally, just with your finger, morning and evening until the pregnancy test.
We advise that you have a day or two off work, resting at home following the egg retrieval.
After egg collection
Cyclogest pessaries
Start using your Cyclogest pessaries tonight. They can be inserted vaginally or rectally. You may find it helpful to use a panty liner. From tomorrow morning, use one pessary every morning and night until your pregnancy test.
Going back to work
We advise you to have 1-2 days off work after your egg retrieval.
Step 5 – Fertilising the eggs and embryo development
We want to give you the best possible chance that the eggs will be fertilised. At the same time, we do not want to carry out any unnecessary interventions.
There are two ways to fertilise the egg. If the sperm count is normal, we place about 100,000 sperm next to each egg in a dish to allow for fertilisation. This is IVF (In vitro fertilisation). If the sperm count is of poorer quality, we inject just one sperm directly into the egg. This is ICSI (intracytoplasmic sperm injection).
ICSI is much more complicated, eggs are assessed for maturity with only mature eggs being injected with sperm, which can lead to a reduced number of eggs being available for treatment (compared to IVF) and costs more than IVF. For these reasons, we prefer to do IVF where possible.
Find out more about Intracytoplasmic sperm injection (ICSI)Failed fertilisation
Failure of fertilisation is unusual. Occasionally, this happens even when both sperm and eggs appear normal. If this happens, we will make you an appointment to see you for individual advice and to discuss further treatment options. You should discontinue using the pessaries.
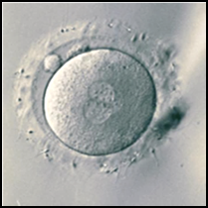
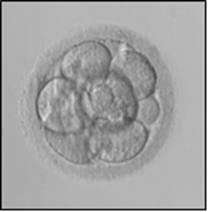
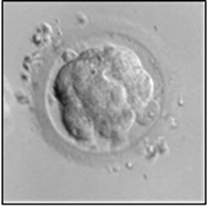
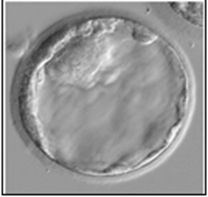
Embryo development
Stages of embryo development
Step 6 – Embryo transfer
All patients will have their embryos cultured to day 5 for embryo transfer. By waiting until day 5 we are confident we can increase pregnancy rates and reduce multiple pregnancies.
Embryo grading prior to your transfer?
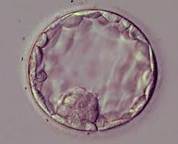
All embryos that have developed to the blastocyst stage will be assessed for quality and categorised:
- Top
- Good
- Fair
- Poor
- Very poor
- Early
The embryologist will be able to give you more information at transfer about your embryos.
Examples of good and early blastocysts

How many embryos do we recommend are transferred?
The number of embryos we recommend to transfer will be based on your age, medical and fertility history and the quality of the embryos on day 5. This is to maximize your chance of success as well as to reduce the risk of a multiple pregnancy.
If you have embryos on day 5 that have not yet reached the blastocyst stage but have developed to a compacted stage embryo (morula), we might recommend having 2 embryos transferred if you are medically fit.
Some women will be restricted to a single embryo transfer to reduce their risk of a multiple pregnancy. This is because their health would be significantly compromised in a multiple pregnancy. We will discuss this with you if it is relevant to you.
Embryos that have not developed beyond the cleavage stage on day 5 do not have the potential to implant so if none of your embryos develop beyond the cleavage stage we are unable to proceed with an embryo transfer. This does not happen very often but is more likely in women aged 40 or over.
What do I/we do before coming in for embryo transfer?
Have your breakfast/lunch as usual then come to the Centre at the time arranged. Please do not wear perfume, aftershave or strong deodorants, as strong smells can be detrimental to your embryos.
What happens when I am admitted?
There may be a little time between your arrival at the Centre and being called for your transfer. Take this time to relax. When called for transfer the embryologist will tell you about your embryos. We will confirm with you again the number of embryos you wish to have transferred.
What happens when the embryos are transferred?
Before your procedure, we will ask you and your partner (if applicable) to cover your clothes with a theatre gown and remove your outside shoes and put on theatre shoes/slippers. In the transfer room, we will confirm your name and check it against your embryo with the embryologist. We will be able to show you your embryo for transfer on the monitor screen if you wish. The procedure usually only takes a few minutes and is usually quick and painless. We will use an ultrasound scanner on your tummy to check the tip of the embryo transfer catheter is in the right place. You may go home straight afterwards as resting or lying down does not improve the success rate. You may also empty your bladder!
Mostly the procedure is straightforward. However, sometimes it may take longer to pass the catheter into the womb. After the embryo transfer procedure the catheter is checked to confirm that the embryos have gone. Occasionally one or more may have stuck inside the catheter and the procedure has to be repeated.
After the embryo transfer
We advise you to lead as normal a life as possible after the transfer without doing anything too strenuous. There is no need to abstain from sexual activity after the embryo transfer. There is nothing more you can do at this stage to help the embryos to implant. Please don’t hesitate to telephone the Centre if you have any problems. Remember that we are here to support you throughout your treatment.
Embryo freezing
Sometimes we have spare embryos to freeze though this is not guaranteed. In fact, most patients do not have spare embryos to freeze. The likelihood of not having embryos to freeze increases with female age so a women aged 32 would be more likely to have spare embryos to freeze than a women aged 38. We will let you know if you have spare embryos to freeze.
We understand that there are different ways to think about your embryos whilst they are in the embryology laboratory and at this very stressful time in your treatment, it may be very difficult to decide whether or not to freeze embryos. The embryologist will discuss the quality and the suitability of your embryos for freezing with you at the time of the embryo transfer. We hope that the information below will help you with this choice.
How does the embryologist decide which embryos are of good quality?
There is no absolute test that tells us whether or not an individual embryo can make a baby. The embryologist will look at the embryos and assess how quickly each embryo is dividing and whether all the cells are dividing evenly. We always transfer the best quality embryos to give the best chance of a pregnancy.
How do we decide whether to offer you embryo freezing?
This decision is based on our experience of how embryos survive freezing.
Freezing and thawing is stressful to the cells of an embryo. For some embryos, all of the cells remain intact while in others all of the cells break up and are no longer viable. Only the best quality embryos are suitable for freezing. Poor quality embryos very rarely survive this thawing process. Thus, we only recommend freezing good quality embryos.
How many people have embryos frozen?
In the UK, no more than 1 in 4 couples will have embryos frozen. This is because not many couples have good quality embryos remaining after embryo transfer. The most likely outcome for you therefore is that you will not have embryos to freeze.
What is the chance that a frozen embryo will make a baby?
We have analysed our results by looking at all the embryos that are frozen. If your embryos survive thawing and are transferred, there is about a 30% chance of pregnancy.
There is no evidence that any babies resulting from thawed embryos have an increased risk of harm or abnormality.
Do we have to pay for freezing?
If you are NHS patients, the cost of freezing is often included in your treatment if freezing is recommended. If you decide to freeze against our recommendations, you may have to pay. The NHS usually funds storage of embryos for one year. Self-funded patients need to pay for embryo freezing. This is an additional charge to your treatment cost.
Ongoing costs
If you have a successful pregnancy, you would then need to pay for embryos to be thawed for further treatment. There is an annual fee for ongoing storage.
The costs of freezing and storage are available in our self-funded patient information.
So should we have embryos frozen?
The decision is yours and will usually depend on how you view your embryos. We hope that the information above has helped you make this decision. The embryologist will talk to you about the quality of your embryos on the day of embryo transfer and you will need to make a decision then. If you want to talk to anyone about this before then please let us know.
What do we do if we want embryos frozen?
You will need to agree to embryo freezing on your consent forms.
What happens to the embryos is they are not frozen?
Embryos that are not suitable for freezing are put into a solution that stops them growing then they are discarded.
Your embryos will not be given to another patient/couple.
Embryos may be donated to research or training but only with your written consent.
What do we have to decide later about the frozen embryos?
If you have embryos frozen, we will contact you each year to ask for your decision about ongoing freezing. If you wish to have the embryos transferred, we will see you both in the clinic to discuss this. 38% of couples decide not to use the
Risks of treatment
Poor response
Sometimes despite our best efforts, the ovaries respond very poorly or not at all to the FSH injections and a difficult decision has to be made about stopping the treatment cycle.
Often this is not unexpected, as you may have been warned that your ovarian reserve was low and that we were concerned that you would not respond to the injections. Sometimes however we are surprised when even with a predicted good response the ovaries do not behave as expected. We know that this is difficult and upsetting news to receive.
Some women will have the opportunity to try again with an increased dose of FSH injections but for those women already on the maximum dose there is nothing more we can do to make the ovaries respond in a better way. If this happens to you, we will explain the scan results in detail and talk about your options. We may ask you to go away and think about the advice we are giving then return to the outpatient clinic at a later date to discuss things further.
Ovarian hyperstimulation syndrome (OHSS)
A small number of women who are having treatment to stimulate the ovaries will develop a problem called ovarian hyperstimulation syndrome (OHSS).
If you wish to know more about our research, we would be happy to discuss this with you when you come to the clinic.
Contact
If you have any questions or concerns throughout your treatment, you can email the fertility nurses.
We do our best to answer your call as soon as possible, but we are a very busy service, so we may not always have someone available to speak with you immediately. If the line is engaged, please try again later or use the nurse email address above. The telephone line is often quieter in the afternoon.
Outside of these hours, there is an on-call doctor available to speak to in emergencies only on 0191 256 8240. The on-call doctor is not able to change clinic appointments or to answer general queries that are not urgent. These types of calls must be made during clinic opening hours.

 For more urgent queries, our telephone line is open 8am to 4.30pm Monday to Friday

Patient feedback
We welcome your opinions and feedback on areas you feel have gone well or suggestions you may have to help us improve our service.
If you have any problems during your treatment or are unhappy with the care you are receiving please contact the Senior Sister (Stacey Turnbull) on 0191 213 8213.
Fertility treatment is sometimes upsetting and frustrating particularly when things do not go quite to plan or you do not get the outcome you had hoped for. Sometimes having a chat with us will help relieve some of the tension and frustrations you may be feeling. We are always willing to listen.


